
"Visual evidence, however compelling, demands microscopic confirmation to avert potentially harmful clinical errors, especially in complex pediatric cases."
This striking medical case highlights the critical importance of rigorous diagnostic confirmation, even when visual cues strongly suggest a particular diagnosis. A seemingly living, worm-like entity discovered within a 13-year-old boy’s bladder, initially presumed to be a parasitic infection, was ultimately revealed to be an unusually shaped blood clot. This misinterpretation, had it led to immediate treatment, could have endangered the boy due to his pre-existing complex medical conditions. The incident serves as a powerful reminder that definitive diagnosis hinges on laboratory analysis, not solely on initial visual impressions, particularly when dealing with patients who have intricate health histories.
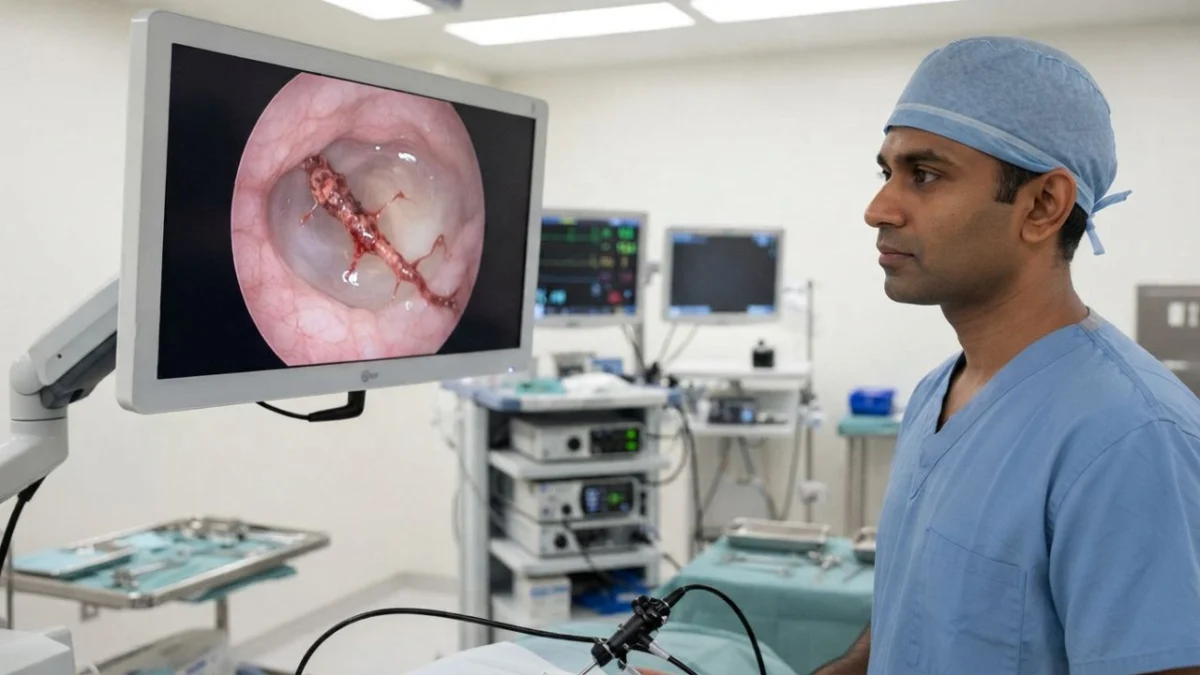
The perplexing discovery unfolded when urologists in Qatar utilized a camera to examine the bladder of a 13-year-old boy experiencing persistent bloody urine for several months. Within the fluid-filled organ, they observed a long, mobile, worm-like structure engulfed in debris. The visual impression was so vivid that the medical team’s initial hypothesis centered on a parasitic infestation. However, the reality, unveiled only after microscopic examination, was far less sinister, yet equally remarkable: the "worm" was, in fact, a blood clot measuring approximately 10 centimeters, or about 4 inches, in length.
This unusual case, documented and published on September 3, 2026, in the esteemed journal Case Reports in Urology, originates from physicians at Hamad Medical Corporation and Sidra Hospital in Doha. The report, aptly titled "A Worm-Like Illusion," underscores a vital principle in medical practice: the imperative to validate even the most convincing visual findings. The authors emphasize that a physician’s initial assessment, while crucial, must always be corroborated by definitive scientific evidence to prevent diagnostic and therapeutic missteps.
The young patient presented a significantly complex medical profile, far from a typical presentation. He was born with hypoplastic left heart syndrome, a severe congenital heart defect characterized by an underdeveloped left ventricle. To address this, he had undergone a Fontan procedure, a palliative surgical intervention designed to reroute blood flow in individuals with single-ventricle physiology. Beyond his cardiac condition, the boy also managed epilepsy, autism spectrum disorder, and immune thrombocytopenia (ITP). ITP is an autoimmune disorder where the immune system mistakenly attacks and destroys platelets, essential components of blood responsible for clotting. His daily medication regimen included aspirin, a blood-thinning agent, and enalapril, a medication for blood pressure management.
For a period of six months preceding his admission, the boy had been experiencing intermittent episodes of significant, visible blood in his urine, a condition known as gross hematuria. His admission was further complicated by a concurrent nosebleed. Diagnostic evaluations upon admission revealed a platelet count of approximately 100,000 per microliter, which falls below the normal range, alongside mild anemia and substantial quantities of blood and protein detected in his urine. Crucially, his urine culture yielded negative results, and standard blood clotting tests appeared within normal parameters. Initial imaging studies, including ultrasound and computed tomography (CT) scans of his kidneys, ureters, and bladder, failed to identify any stones, masses, or structural abnormalities. Given the inconclusive nature of these imaging modalities, the medical team opted for cystoscopy, a procedure that allows for direct visualization of the interior of the bladder.
The elongated morphology and the perceived motion of the object within the bladder strongly suggested the possibility of parasitic infections to the medical team. Two parasitic diseases that can cause such symptoms were at the forefront of their differential diagnoses: schistosomiasis and filariasis. Schistosomiasis, in particular, is a well-established cause of bloody urine globally. The World Health Organization (WHO) reported that in 2024, an estimated 253.7 million individuals required preventive treatment for this disease, with approximately 94% of these cases concentrated in Africa. Infection occurs through direct contact with freshwater contaminated with larval forms of the parasite, which are released from freshwater snails. The larvae then penetrate the skin, and in the urogenital form of the disease, blood in the urine is a classic hallmark. The Centers for Disease Control and Prevention (CDC) also notes that schistosomiasis, also known as bilharzia, affects over 200 million people worldwide and is typically diagnosed through stool, urine, or blood tests.
However, several factors cast doubt on the schistosomiasis diagnosis in this specific case. The boy had no history of travel to endemic regions where the parasite is prevalent, nor did he report any exposure to freshwater environments. Furthermore, his eosinophil count, a type of white blood cell that often elevates in response to parasitic infections, was within the normal range. A specific urine test for Schistosoma haematobium, the parasite responsible for urogenital schistosomiasis, returned negative.
Following the visual examination, the surgical team proceeded to remove the enigmatic structure from the boy’s bladder. It was subsequently sent for pathological analysis. The verdict from the pathology laboratory was definitive: the "worm" was an organized blood clot, primarily composed of fibrin, the protein that forms the structural framework of blood clots, densely packed with red blood cells. Microscopic examination revealed no evidence of parasites or any signs indicative of malignancy.
The authors of the case report offer a compelling explanation for how a blood clot could manifest as a worm-like entity. They elucidate that in individuals with platelet disorders, such as ITP, fibrin clots can indeed form elongated, thread-like structures within the bladder. Additionally, the turbulent flow of urine, a phenomenon that can occur in patients with Fontan circulation due to altered hemodynamics, may further stretch and distort these clots. In this particular boy’s case, the confluence of his low platelet count and the use of aspirin is believed to have contributed to ongoing bleeding and the subsequent formation of the elongated clot. The report does not pinpoint a specific renal etiology for the initial bleeding.
The phenomenon of blood clots mimicking worms is not entirely unprecedented. In 2025, a report published in the Journal of Medical Case Reports described a similar incident involving a 77-year-old man in France. He presented with a black, worm-like object found in his urine collection bag, which was also identified as a blood clot. The authors of that report attributed its shape to the tubular structure of the urethra.
The Qatar-based medical team issued a stern warning regarding the potential ramifications of misidentifying such an object. They emphasized that initiating antiparasitic drug treatment, such as praziquantel or albendazole, based solely on visual appearance could have exposed the boy to significant risks. Given his pre-existing cardiovascular and hematological comorbidities, he could have experienced adverse drug reactions, potentially exacerbating his already precarious health status. The authors’ overarching conclusion is unequivocal: "No matter how convincing visual findings may seem, they should always be backed by microscopic evidence to prevent clinical errors."
Following the successful removal of the clot, the boy’s bleeding gradually subsided over the course of his nine-day hospitalization. He was discharged without further episodes of hematuria. His antiplatelet therapy was subsequently adjusted, though the specifics of this adjustment and any long-term follow-up are not detailed in the published report.
This case, with its intricate interplay of rare medical conditions, does not suggest that worm-like blood clots are a common occurrence in pediatric patients. It is important for parents to understand that blood in a child’s urine, particularly when asymptomatic, is often benign. StatPearls, a clinical reference resource from the National Library of Medicine, notes that microscopic hematuria (blood in urine detectable only by testing) without symptoms is found in approximately 4% of healthy school-aged children and rarely signifies cancer.
Nevertheless, the presence of visible blood, especially when accompanied by clots, warrants prompt medical evaluation. MedlinePlus, a health information service from the National Library of Medicine, lists blood-thinning medications like aspirin and low platelet counts among the potential causes of bloody urine. The resource strongly advises seeking immediate medical attention when an individual passes blood clots in their urine, underscoring the need for thorough investigation and accurate diagnosis.
Key Questions Answered
What did doctors find in the boy’s bladder?
Doctors discovered a long, worm-like structure, approximately 10 centimeters in length, which appeared to move within the fluid of the bladder. Subsequent pathological examination revealed it to be an organized blood clot composed of fibrin and red blood cells.
Why did they suspect a parasite?
The unusual elongated shape and the apparent motion of the object strongly resembled parasitic worms. This led the medical team to consider parasitic diseases like schistosomiasis, a significant cause of bloody urine in many parts of the world, particularly Africa.
What caused the bleeding?
The authors of the report hypothesize that the boy’s bleeding was likely a consequence of his low platelet count, stemming from immune thrombocytopenia, combined with his aspirin therapy. The report does not identify a specific cause of bleeding within the kidneys themselves.
Why does the misdiagnosis matter?
Mistaking the blood clot for a parasitic worm and initiating treatment with antiparasitic drugs could have exposed the boy to unnecessary medications and potentially severe side effects, especially given his complex pre-existing heart and blood-related health conditions.
Should parents worry about blood in a child’s urine?
While asymptomatic microscopic blood in a child’s urine is often harmless, visible blood or the passage of blood clots should always be evaluated by a healthcare professional to determine the underlying cause and ensure appropriate management.
