
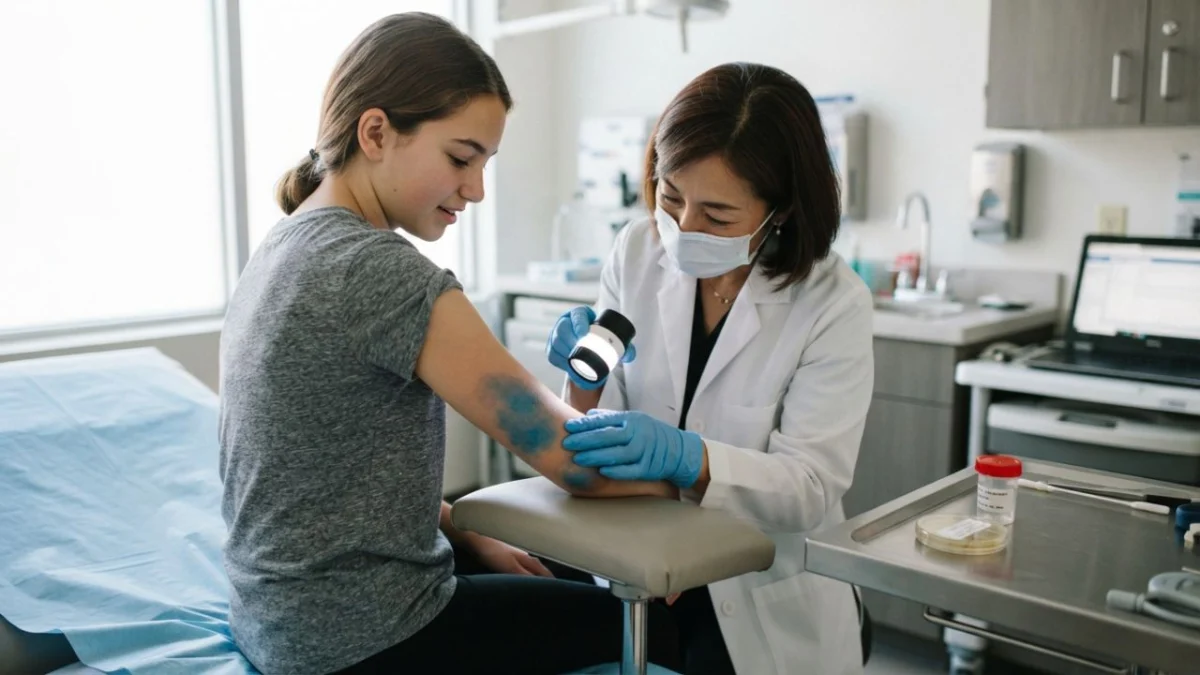
"A puzzling blue discoloration on a teenager’s arm, initially alarming enough to warrant extensive cardiac and medical workups, was ultimately traced not to a failing heart or lungs, but to bacteria on her skin turning clear sweat into a colorful phenomenon."
This extraordinary case highlights the diagnostic labyrinth that can sometimes accompany unusual medical presentations. While blue skin often triggers immediate concern for serious conditions like cyanosis, this report underscores the importance of considering less common explanations, such as pseudochromhidrosis, a condition where sweat itself becomes colored after contact with the skin’s surface. The extensive evaluation the patient underwent before arriving at this diagnosis serves as a potent reminder that sometimes, the answer lies not within the body’s core functions, but on the very surface of our skin.
A 17-year-old girl’s right elbow and upper arm presented a perplexing medical mystery, exhibiting intermittent bright blue discoloration. This striking hue, which would appear and then fade, was particularly concerning given the patient’s history of orthopedic injuries in the affected area. The unusual presentation prompted a comprehensive diagnostic investigation involving multiple specialists. Extensive imaging, detailed laboratory workups, and even a thorough cardiac evaluation were conducted in an effort to pinpoint the cause of the alarming color change. To the perplexity of the medical team, all these rigorous examinations returned normal results, leaving the underlying cause of the blue skin elusive.
The breakthrough in diagnosis came not from advanced medical technology or invasive procedures, but from a simple microbiological test. A bacterial culture from the affected skin revealed the presence of a color-producing organism. This finding led to a diagnosis of pseudochromhidrosis, a rare condition characterized by clear sweat that acquires color only after it reaches the skin’s surface. The treatment, a course of antibiotics, proved remarkably effective, completely eradicating the blue discoloration. This resolution was documented in a 2026 case report published in the Journal of Pediatric Health Care, titled "A Case of the Blues: Pseudochromhidrosis in an Adolescent Following Injury." The report’s overarching message emphasizes the prolonged diagnostic journey the patient experienced before the seemingly innocuous source of her symptom was identified.
The instinct to immediately investigate the heart when faced with blue skin is deeply ingrained in medical practice. This is due to the well-established association between a bluish tint to the skin or mucous membranes and a lack of oxygen in the blood, a condition medically termed cyanosis. According to MedlinePlus, the National Library of Medicine’s health information website, cyanosis can be a critical indicator of serious underlying health issues. These can include congenital heart defects, heart failure, severe lung disease, or airway obstruction, all of which can compromise oxygenation and necessitate urgent medical intervention.
In the case of the 17-year-old, however, the presentation deviated significantly from the typical profile of cyanosis. The discoloration was not generalized but localized to a specific area—her elbow and upper arm—and its intermittent nature further complicated the diagnostic picture. The fact that this area had a prior history of orthopedic injuries added another layer of complexity, leading clinicians to consider a broad differential diagnosis and meticulously rule out various potential causes.
The report details an exhaustive evaluation undertaken by a multidisciplinary team of specialists. Despite the thoroughness of the imaging, cardiology assessment, and laboratory tests, no definitive cause was identified. The published summary does not specify the duration of this diagnostic odyssey or list every specialist involved, but it highlights the extensive nature of the workup. Ultimately, it was a microbiology test, rather than a cardiac scan or other advanced diagnostic tool, that provided the crucial clue. A bacterial culture indicated the presence of a chromogenic organism, a type of microbe capable of producing color, which is consistent with pseudochromhidrosis. The specific bacterial species responsible for the blue hue in this particular case was not named in the summary.
Pseudochromhidrosis belongs to a broader category of conditions known as chromhidrosis, which refers to the presence of colored sweat. Medscape’s clinical overview of chromhidrosis categorizes it into three main forms. Apocrine chromhidrosis involves certain sweat glands that secrete pigmented substances. Eccrine chromhidrosis, a much rarer form, is associated with the ingestion of specific dyes or medications that tint the sweat. Pseudochromhidrosis, on the other hand, is distinct because the body’s sweat glands function normally, producing clear sweat. The coloration occurs externally, on the skin’s surface, due to external factors. As Medscape explains, in pseudochromhidrosis, "clear eccrine sweat becomes colored on the surface of the skin as a result of extrinsic dyes, paints, or chromogenic bacteria."
This distinction is clinically significant. In pseudochromhidrosis, the abnormality lies not within the body’s internal secretions but in the interaction of clear sweat with an external pigment source, most commonly microbes that colonize the skin. A 2020 case report and literature review published in Acta Dermato-Venereologica by Norwegian researchers identified four bacterial species known to cause the infectious form of colored sweat, each associated with a characteristic color: Bacillus species (blue), Pseudomonas aeruginosa (blue-green), Corynebacterium species (brown or black), and Serratia marcescens (red or pink).
The medical community continues to expand this list of causative agents. In a March 2026 report in Cureus, Brazilian physicians documented a case where an 88-year-old man’s blue sweat and skin staining were linked to Pseudomonas stutzeri within an infected leg wound. The authors noted that their literature review revealed no prior reports associating this specific bacterial species with pseudochromhidrosis. Medscape further emphasizes the rarity of chromhidrosis in general, noting the absence of reliable incidence figures.
The treatment for the teenage patient involved a combination of systemic erythromycin, an antibiotic administered orally to work throughout the body, and topical clindamycin, applied directly to the skin. This therapeutic approach proved highly successful, leading to the complete resolution of the blue discoloration, with no recurrence reported. While the specific dosages and duration of treatment were not detailed in the summary, this combination has precedent in managing similar conditions. In the aforementioned Norwegian study, two adult patients experiencing blue discoloration due to Bacillus cereus were treated with oral erythromycin (250 milligrams three times daily) and topical clindamycin (twice daily) for 10 days. Both patients achieved complete remission, with no relapse observed during a six-month follow-up period. The objective of such treatment is to eliminate the color-producing bacteria, thereby normalizing the skin’s appearance, rather than altering the sweat’s composition itself.
The Norwegian review also offered practical diagnostic recommendations, advocating for bacterial testing as the primary step in evaluating colored sweat or unusual skin discoloration. They highlighted simple bedside clues that could aid in diagnosis. The blue pigment, they noted, "could be removed with soap and water; however, it was more easily removed with alcohol wipes." Additionally, a Wood’s lamp, a handheld ultraviolet light, could reveal fluorescence on the affected skin. Whether these specific diagnostic aids were employed in the teenager’s case was not mentioned in the summary.
The case report frames the patient’s experience as a valuable diagnostic lesson, highlighting pseudochromhidrosis as an underrecognized cause of unusual skin discoloration. The authors suggest that its inclusion on clinicians’ differential diagnoses could spare patients from extensive, potentially unnecessary testing and expedite appropriate treatment.
It is crucial to acknowledge the limitations of this case report. As a single case study, it cannot definitively establish a causal link between the patient’s prior injuries and the development of pseudochromhidrosis. While the title of the report connects the discoloration to previous injuries, a single instance does not provide sufficient evidence to prove that trauma triggers the condition. Furthermore, the published summary leaves several questions unanswered, including the precise bacterial species responsible, the reasons for the intermittent nature of the color change, and whether the earlier injuries played any direct role in the skin’s susceptibility to bacterial colonization or pigment production.
Despite these limitations, the case serves as an important reminder that blue skin should not be summarily dismissed. Cyanosis, indicative of low blood oxygen levels, can signal life-threatening conditions, and MedlinePlus strongly advises seeking emergency care for bluish skin accompanied by difficulty breathing, chest pain, confusion, or unusual drowsiness. Ruling out these grave possibilities remains a cornerstone of standard medical practice.
What this particular case adds to the medical discourse is a compelling illustration that sometimes, unusual skin coloration originates not from within the body’s complex physiological systems, but from external factors interacting with the skin’s surface. For individuals experiencing unexplained skin or sweat discoloration, consulting a healthcare professional is paramount. A clinician can then determine the most appropriate diagnostic pathway, which may include microbiological cultures or other specialized investigations, to accurately identify the cause and initiate effective treatment.
