
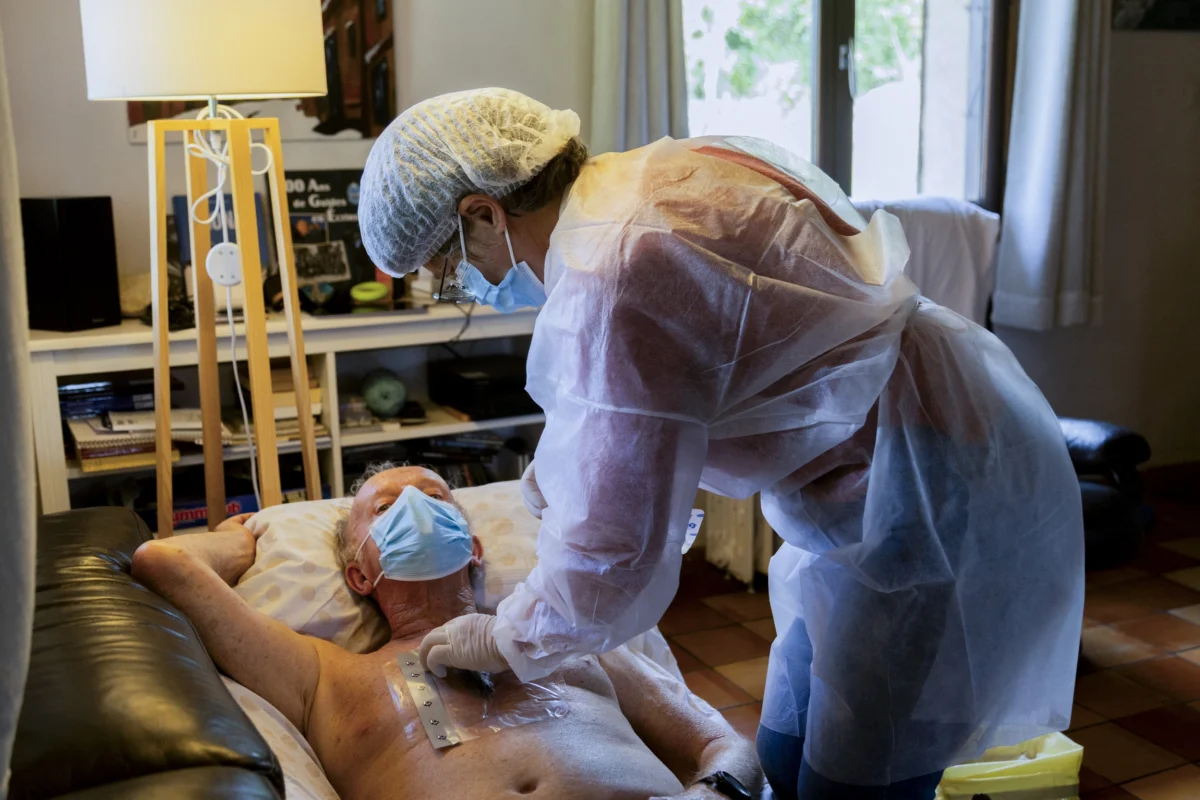
"Even with a strong early track record and extended federal support, Cone Health’s decision to end its hospital-at-home program underscores the complex financial and operational hurdles that continue to challenge the sustainability of this innovative care model."
Cone Health, a prominent health system based in Greensboro, North Carolina, has announced the discontinuation of its hospital-at-home program, a move that signals a broader industry-wide reevaluation of the model’s long-term viability. This decision comes despite the program’s initial success, including zero patient deaths and no reported healthcare-associated infections in its first year of operation. The program, designed to provide acute hospital-level care within patients’ residences, will be phased out by the end of the fourth quarter, with provisions made to ensure continuity of care for existing patients during the transition. The closure raises critical questions for patients and policymakers about the dependability and future of hospital-at-home services, particularly as the program’s discontinuation occurs even with an extended federal waiver supporting such initiatives.
Launched in April 2025, Cone Health’s hospital-at-home initiative was initially a modest program, capped at six patients simultaneously. Its early performance metrics, detailed in a June 1 release, were remarkably positive, showcasing a commitment to high-quality patient outcomes. The system had planned for expansion, contingent on broader insurer adoption and reimbursement. However, Cone Health’s statement cited a confluence of factors contributing to the decision, including shifting reimbursement landscapes, increasing operational complexities, and inherent uncertainties regarding the long-term financial sustainability of the model. This sentiment echoes concerns voiced by health systems nationwide as they grapple with the practicalities of implementing and scaling these advanced care settings. Cone Health expressed pride in the care delivered and gratitude for its dedicated staff, affirming that personnel would be redeployed and that current patients would receive uninterrupted care.
The operational framework for hospital-at-home programs is largely underpinned by Medicare’s Acute Hospital Care at Home waiver. This federal provision, initially established during the COVID-19 pandemic, allows certain Medicare beneficiaries with conditions like heart failure, pneumonia, or infections to receive hospital-level care in their homes. This care encompasses daily clinical visits, sophisticated remote monitoring technologies, and rapid response capabilities should a patient’s condition deteriorate. The waiver, however, has navigated a turbulent history, marked by periods of uncertainty that have complicated long-term strategic planning for health systems. A notable instance occurred during a federal government shutdown, which necessitated the immediate discharge or transfer of Medicare patients enrolled in these programs, leading to operational scrambles and patient displacement, as reported by Becker’s.
In an effort to provide greater stability, Congress extended the waiver through September 30, 2030, as part of the Consolidated Appropriations Act, 2026, signed into law on February 3, 2026. This extension offers a five-year runway, a significant improvement from previous iterations. As of March 2026, the American Medical Association reported that 366 hospital-at-home programs had received approval across 139 health systems in 37 states, indicating a growing adoption of the model.
Despite the extended waiver, the path to widespread and stable implementation remains fraught with challenges. The waiver, while a crucial support mechanism, does not guarantee permanent Medicare coverage beyond its expiration date. Furthermore, the reimbursement terms offered by many commercial insurers often differ from Medicare, creating financial disparities that can hinder program scalability. These inconsistencies can leave programs struggling to attract sufficient patient volume to offset the significant operational costs associated with maintaining round-the-clock care, specialized staffing, and advanced technological infrastructure.
The financial architecture of hospital-at-home programs presents a unique set of demands. Unlike traditional hospital units where fixed costs can be distributed across a larger patient base, hospital-at-home models require dedicated resources that must be allocated to a smaller, more mobile patient population. These costs include mobile clinical teams available at any hour, efficient logistics for medication and laboratory sample delivery, investment in robust remote monitoring equipment, and the continuous operation of a central command center. For programs with limited patient capacity, these expenditures can quickly outpace revenue, jeopardizing financial sustainability.
The human element of this uncertainty is also significant. Healthcare administrators and clinicians involved in these programs have openly discussed the psychological toll of operating under fluctuating policy landscapes. Dr. Michael Nassif, medical director of Saint Luke’s Hospital In Your Home in Kansas City, previously articulated the strain that program instability places on administrators, particularly those responsible for managing full-time staff.
Despite these headwinds, the hospital-at-home movement is not without its momentum. Several major health systems are actively expanding or launching new programs. NewYork-Presbyterian initiated a program in Manhattan in November 2025, Penn Medicine is implementing its model across three hospitals, and Cleveland Clinic has successfully cared for approximately 3,000 patients since 2023, with plans to extend its reach into Florida. Tampa General Hospital has also reported promising early data suggesting lower readmission rates for its program, though specific figures have yet to be released.
For patients, the closure of a hospital-at-home program represents a loss of a preferred care option. This demographic often includes older adults, individuals with mobility limitations, and those with caregivers who find regular hospital visits challenging. For these patients, the discontinuation of home-based care may necessitate a return to traditional hospital admissions, potentially leading to longer wait times in emergency departments, especially during periods of high hospital occupancy.
Patients currently enrolled in programs that are winding down are advised to proactively communicate with their care teams. Key questions to address include the logistics of follow-up appointments, prescription management, the return of any borrowed medical equipment, and the designated contact for after-hours support. Prospective patients considering hospital-at-home care elsewhere should inquire about their insurance coverage, the protocol for managing worsening conditions, and the expected response time for clinical visits.
It is critical to reiterate that hospital-at-home care is not designed for acute medical emergencies. Symptoms such as severe chest pain, difficulty breathing, sudden onset of confusion, or indications of a stroke require immediate emergency medical attention, and individuals experiencing these should call 911 without delay. The ultimate success and permanence of the hospital-at-home model will hinge on evidence gathered and presented to Congress before the waiver’s expiration in 2030. Cone Health’s decision underscores that beyond federal waivers, factors such as consistent payer reimbursement, robust patient volume, and efficient staffing models will be the true determinants of which programs can achieve lasting sustainability.
