
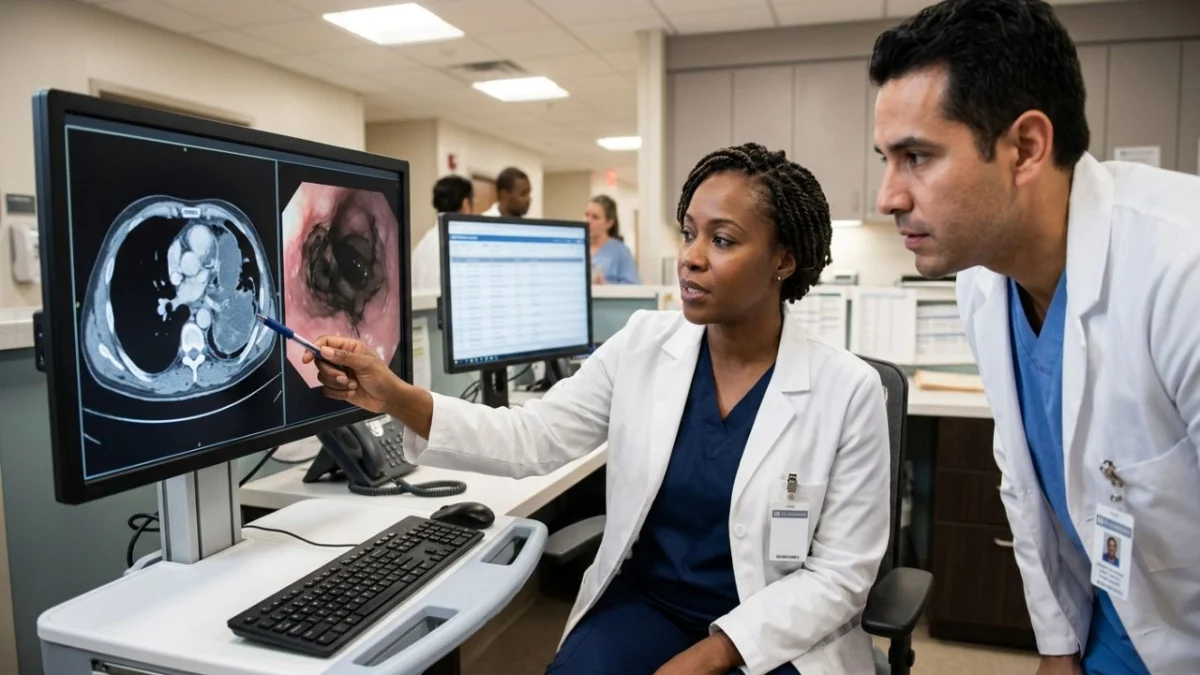
"A large hiatal hernia can pose a silent, life-threatening risk, leading to gastric volvulus and a rare condition known as ‘black esophagus’ even without prior digestive distress."
This case report highlights a stark reminder of how seemingly unrelated medical issues can converge with devastating consequences. An 87-year-old woman, hospitalized for pelvic fractures, was found to have a life-threatening condition developing silently within her: a large hiatal hernia causing her stomach to twist, a phenomenon known as gastric volvulus. This twist, in turn, led to acute esophageal necrosis, or "black esophagus," a rare and often fatal complication characterized by the death of esophageal tissue. The case, published in Cureus, underscores the potential for catastrophic outcomes from overlooked anatomical abnormalities and the critical need for vigilance in recognizing atypical presentations of serious illness.
The unexpected discovery occurred during a routine CT scan for the patient’s pelvic injuries. Contrary to what might be expected for an elderly patient with pelvic trauma, her symptoms were not indicative of digestive distress. She presented with no gastrointestinal complaints whatsoever. However, the imaging revealed a significant paraesophageal hernia, a condition where a portion of the stomach protrudes through the diaphragm alongside the esophagus and into the chest cavity. This anatomical anomaly had allowed her stomach to rotate on its long axis, a specific type of gastric volvulus termed organoaxial. Doctors suspected this twisting had obstructed the outlet of her stomach.
The case, authored by Roy Arslan Ahmed, is particularly striking due to the absence of prodromal symptoms. The severe complication developed without the typical warning signs that might alert clinicians to gastrointestinal compromise. The patient’s condition took a sudden and dramatic turn when she experienced acute hypoxemic respiratory failure, a dangerous decline in blood oxygen levels. During emergency intubation, a critical procedure to secure her airway, a significant volume of dark, coffee-ground-like material was aspirated into her lungs, strongly suggesting a massive outpouring of upper gastrointestinal contents.
Prompt bedside intervention, including an upper endoscopy, was performed. This procedure revealed that the gastric volvulus had been reduced, relieving a functional obstruction in the upper third of her esophagus. However, the endoscopy also unveiled a grim and rare finding: extensive blackening of the esophageal lining, a condition known as acute esophageal necrosis, or "black esophagus." This necrosis, characterized by dead and blackened tissue, circumferentially enveloped the organ and extended upwards. Despite aggressive supportive care, the patient’s condition deteriorated rapidly. She developed septic shock and subsequent failure of multiple organ systems, ultimately leading to her death after her care was transitioned to comfort-focused measures.
Acute esophageal necrosis is a rare condition, with reported incidences ranging from a mere 0.008% to 0.2% according to a 2026 case report in Oxford Medical Case Reports. The characteristic endoscopic appearance is that of a black, fragile esophageal lining, with the damage typically ceasing abruptly at the junction of the esophagus and stomach. This condition was first described at autopsy in 1967 and subsequently observed via endoscopy in 1990. The pathogenesis is believed to involve a confluence of factors, including compromised blood flow to the esophageal wall, damage to its protective mucosal lining, and exposure to refluxed gastric contents, as outlined in the widely utilized clinical reference, StatPearls. It is sometimes referred to as Gurvits syndrome, named after gastroenterologist Grigoriy Gurvits, who led a significant 2007 review of 88 patients. This review indicated a male predominance, with men affected approximately four times more often than women, and reported an overall mortality rate of around 32%. Crucially, it was noted that the majority of these fatalities stemmed from the underlying comorbidities rather than the esophageal necrosis itself, with StatPearls estimating that direct causation by necrosis accounts for only about 5% of deaths. This pattern aligns with the reported case, where the patient’s demise was attributed to sepsis and subsequent organ failure.
The Oxford Medical Case Reports authors identified several risk factors associated with acute esophageal necrosis, including binge drinking, diabetic ketoacidosis, connective tissue disorders, malignancy, and fungal infections. They emphasized that esophageal tissue deprived of adequate blood supply becomes more susceptible to the damaging effects of gastric acid. In the context of the current case, the gastric volvulus likely created a scenario of critical ischemia, compromising blood flow to the esophagus and rendering it vulnerable to necrosis, particularly when exacerbated by aspiration of stomach contents.
Obstruction within the gastrointestinal tract emerges as a recurring theme in cases of black esophagus. A case presented by physicians at Montefiore Medical Center involved a 58-year-old man with type 2 diabetes who, following a two-month period of significant weight loss and escalating nausea, developed acute esophageal necrosis concurrently with ketoacidosis and duodenal ulcers. The presenters hypothesized that a combination of gastric outlet obstruction, reflux, vomiting, dehydration, and diabetic vasculopathy may have collectively led to esophageal ischemia, even in the absence of overt shock. His CT scan revealed thickened lower esophagus and upper small intestine, with a markedly distended stomach. Persistent severe abdominal pain, even after his ketoacidosis resolved, prompted an endoscopy that ultimately identified the blackened esophagus. This case highlighted the importance for clinicians to maintain a broad differential diagnosis for patients whose symptoms defy conventional treatment approaches.
Management of acute esophageal necrosis is primarily supportive. The authors of the Oxford Medical Case Reports detailed treatment strategies involving intravenous fluid resuscitation and acid-suppressing medications, with the overarching goal of addressing the underlying causative condition. The insertion of nasogastric tubes is generally avoided due to the risk of esophageal perforation. In their reported patient, a follow-up endoscopy four weeks later indicated significant healing of the esophageal lining.
For families and healthcare providers caring for older adults, particularly those with known hiatal hernias, this case serves as a potent reminder of the potential for large paraesophageal hernias to precipitate severe and life-threatening complications with little to no warning. Individuals experiencing symptoms such as vomiting of dark or coffee-ground material, the passage of black stools, sudden onset of severe chest or upper abdominal pain, or acute respiratory distress should seek immediate emergency medical attention. The insidious nature of gastric volvulus, especially when associated with a paraesophageal hernia, can lead to rapid deterioration, as tragically demonstrated in this instance. Early recognition of such anatomical predispositions and prompt intervention when symptoms arise are paramount in mitigating the severe risks associated with these rare but devastating conditions.
